A twisted ankle is not always a simple sprain, and the ability to walk does not prove that no bone, tendon, or ligament is seriously injured. Use the warning signs, time limits, and symptom patterns below to decide between emergency care, early home protection, and a planned evaluation by a foot and ankle specialist.
Key takeaways
- Seek emergency care for deformity, an open fracture, a cold foot, absent pulses, numbness, or severe disproportionate pain.
- Use protection, rest, ice, compression, and elevation during the first 24 to 48 hours.
- Persistent swelling, instability, locking, or inability to bear weight warrants specialist evaluation.
- An examination and targeted X-rays or MRI can reveal injuries a routine sprain assessment misses.
Which foot and ankle injuries need emergency care?
Treat these signs as an ankle injury emergency: a visibly deformed ankle, an open wound over a suspected fracture, a cold or blue foot, loss of pulses, new numbness or weakness, or severe pain out of proportion to the injury. They can signal an unstable fracture-dislocation, blood-vessel or nerve damage, or compartment syndrome.
Rapidly increasing swelling after a high-impact injury also needs immediate assessment.
| Situation | What it can mean | What to do |
|---|---|---|
| Visible deformity or open fracture | Unstable fracture-dislocation | Go to an emergency department now |
| Pale, blue, or cold foot; absent pulses; new numbness or weakness | Circulation or nerve damage | Seek emergency assessment immediately |
| Severe disproportionate pain or rapidly increasing swelling | Possible compartment syndrome | Do not wait for a routine appointment |
| Hot, red, rapidly worsening foot or ankle | Infection, gout, fracture, or Charcot neuroarthropathy | Seek urgent assessment, especially with fever, a wound, diabetes, or reduced sensation |
After an acute injury, the Ottawa Ankle Rules support an X-ray when you cannot take four steps both immediately afterward and during assessment, or when pressing the back edge or tip of either ankle bone, the base of the fifth metatarsal, or the navicular on the inner midfoot causes tenderness.
These findings describe common broken ankle symptoms, but they do not replace emergency care for deformity, an open wound, or circulation or sensation changes.
Diabetes, neuropathy, poor circulation, and previous foot ulcers lower the threshold for urgent evaluation because reduced sensation can hide a serious injury.
What should you do during the first 24 to 48 hours?
During the first 48 hours after an ankle injury, protect the joint rather than testing it. Wear a brace or supportive shoe, or use temporary crutches. Limit weight-bearing after ankle injury if walking increases pain.
- Use ice for an ankle sprain with a cold pack wrapped in cloth for 15 to 20 minutes. Leave several hours between applications, and never place ice directly on your skin.
- Elevate your foot above heart level while resting. This helps control swelling.
- Once severe pain settles, move the ankle gently through a comfortable range to limit stiffness. Do not force the joint or repeatedly test whether it can bear weight.
- Avoid massage, hot baths, heating pads, and alcohol while swelling is acute. Each can increase blood flow and worsen swelling.
Arrange an evaluation if pain continues beyond a few days, swelling is not settling, or you still cannot walk normally. Home treatment is not a diagnosis: you can walk on a fracture, high-grade ligament tear, Lisfranc injury, or stress fracture.
Stop running and impact exercise when pain is focal or progressively worsening, even if rest briefly relieves it. A stress fracture can worsen with continued impact, while a normal early X-ray may not show it. Persistent focal pain needs assessment rather than repeated return-to-run tests.
Which symptom patterns point beyond a routine sprain?
A routine sprain usually follows a twist and causes outer-ankle pain, bruising, and swelling. The sprain versus fracture question becomes more important when pain is sharply localised, weight-bearing is difficult, or symptoms do not steadily improve.
| Pattern | What it may indicate | What to do |
|---|---|---|
| Pain with resisted movement or loss of strength | Tendon injury | Arrange a foot and ankle assessment |
| Pop at the back of the ankle, a kicked sensation, inability to push off, or weakness on stairs | Achilles tendon rupture | Seek prompt evaluation; delayed diagnosis can complicate treatment |
| Focal pain that increases with running or jumping and eases with rest | Stress fracture foot | Stop impact exercise; early X-rays can look normal |
| Midfoot swelling, sole bruising, pain when stressing the forefoot, or difficulty bearing weight after a twist or crush | Lisfranc injury symptoms | Seek specialist assessment; the first X-ray can miss it |
| Burning, tingling, electric pain, or numbness | Nerve involvement | Arrange evaluation rather than testing the injury repeatedly |
A hot, red, markedly swollen joint is not automatically a sprain. Infection, gout, fracture, and Charcot neuroarthropathy can produce this pattern, particularly with diabetes or reduced sensation.
Book evaluation when pain recurs, occurs at night, changes your walking pattern, or lasts beyond about 6 to 8 weeks. Persistent swelling, catching, or giving way after a sprain can indicate chronic ligament instability, an osteochondral lesion, tendon damage, syndesmotic injury, or an occult fracture.
What will a foot and ankle evaluation and imaging involve?
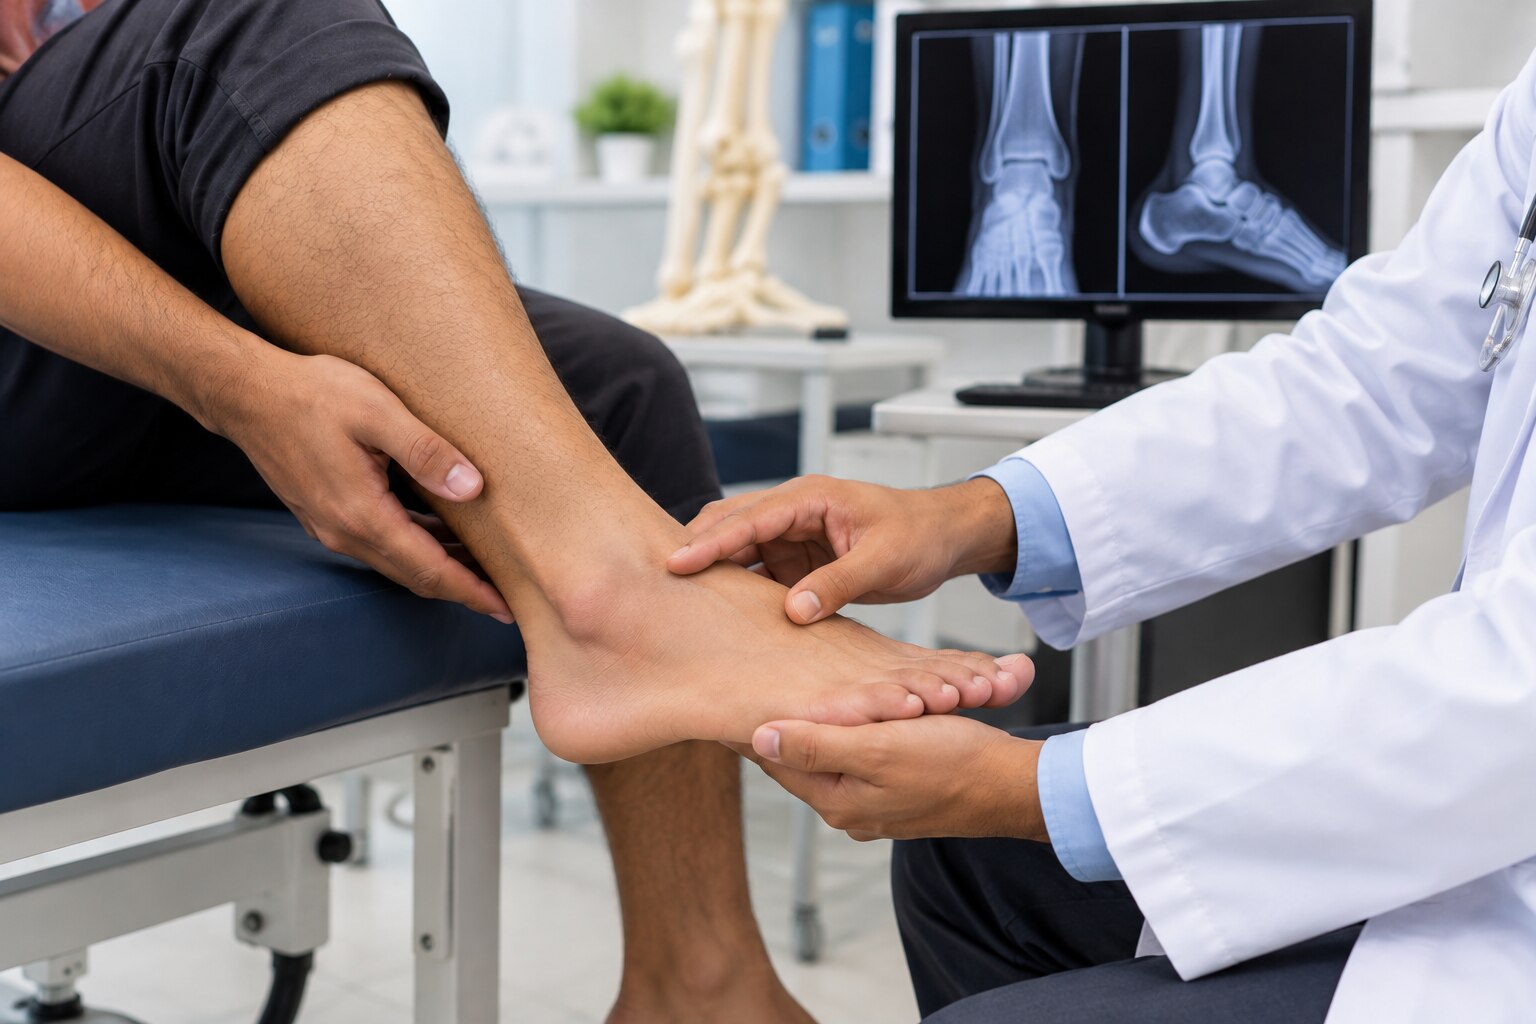
A foot and ankle specialist examination begins with how the injury happened, when you first managed four steps, and whether pain is focal or diffuse. Explain any change in footwear, sport, work, or training before symptoms began.
Tell the clinician about diabetes, neuropathy, poor circulation, immune suppression, previous ulcers, or repeated sprains; these conditions lower the threshold for urgent assessment.
The examination may include:
- Walking and gait assessment
- Weight-bearing alignment
- Swelling and bruising
- Joint range of motion
- Tendon strength
- Ligament stability
- Skin temperature, pulses, circulation, and sensation
An ankle X-ray is usually the first study when fracture criteria are present. It shows bone alignment, obvious breaks, and some arthritis. Suspected Lisfranc injury requires weight-bearing and comparison views because a normal non-weight-bearing film can miss midfoot instability.
An ankle ultrasound can assess the Achilles and other tendons while they move, and the Thompson test can support an Achilles rupture diagnosis. An ankle CT provides detailed views of complex fractures and midfoot alignment.
MRI is useful when X-rays do not explain persistent symptoms or when clinicians need to assess an occult fracture, cartilage or osteochondral injury, syndesmotic or ligament damage, or tendon pathology. MRI is not automatically required for every sprain.
When does specialist care change the treatment plan?
Specialist care changes the plan when symptoms do not follow the expected course of a straightforward injury. Most uncomplicated lateral ankle sprains improve with protection or bracing, progressive weight-bearing as tolerated, range-of-motion exercises, strengthening, and balance training through structured ankle sprain rehabilitation.
Arrange specialist review when:
- Sprains keep recurring, because this pattern can indicate chronic ankle instability. Bracing and neuromuscular rehabilitation can reduce recurrence; ligament repair or reconstruction is considered when instability remains demonstrable and limits function after rehabilitation.
- An Achilles rupture, suspected Lisfranc injury, or stress fracture is possible.
- Pain remains unexplained after a normal X-ray, or pain, swelling, catching, or giving way lasts beyond 6 to 8 weeks.
- Persistent symptoms alter your walking pattern or prevent normal work, exercise, or daily activity.
Advanced ankle arthritis causes deep activity-related pain, stiffness, reduced walking tolerance, and loss of motion. When non-surgical ankle arthritis treatment no longer preserves function, discussions may include ankle fusion or total ankle replacement. The choice depends on deformity, bone quality, activity demands, and adjacent-joint disease; neither operation is routine treatment for a recent sprain.
For people searching for a foot and ankle specialist Mira Road, Dr. Santosh Pandey can assess persistent symptoms and match examination or imaging findings to a clear treatment plan.
Related services
Hand and Foot Care by Dr. Santosh Pandey, Orthopedic Surgeon Our hands and feet are essential for everyday activities, from walking and exercising to working and... View service → |
Physical Examinations ## Physical Examinations Physical examinations are a fundamental part of orthopaedic care, helping specialists assess your overall musculoskeletal... View service → |
Frequently asked questions
Which foot and ankle injuries need emergency care?
Seek emergency care for a visibly deformed ankle, an open wound over a suspected fracture, a cold or blue foot, absent pulses, new numbness or weakness, or severe pain out of proportion to the injury.
What should you do during the first 24 to 48 hours after an ankle injury?
Protect the ankle, reduce weight-bearing, apply ice in short sessions with a cloth barrier, use compression without causing numbness or colour change, and elevate the foot above heart level.
Which symptoms suggest more than a routine ankle sprain?
Inability to take four steps, worsening pain or swelling, repeated giving-way, locking, tenderness over the ankle bones, persistent bruising, numbness, or symptoms that do not improve need evaluation.
What happens during a foot and ankle evaluation?
A specialist checks alignment, swelling, bruising, skin temperature, pulses, sensation, strength, range of motion, and areas of tenderness, then orders imaging based on the findings.
When can specialist care change the treatment plan?
Specialist care can identify fractures, tendon or ligament tears, cartilage injuries, nerve or blood-vessel problems, or instability that require a boot, cast, reduction, surgery, or structured rehabilitation instead of routine sprain care.
Related services
Pain Management for Joint, Back, Knee, and Neck Pain Pain Management for Joint, Back, Knee, and Neck Pain Pain in the joints, back, knees, and neck can significantly affect your daily activities, mobility, and overall quality of life. View service → |
Trauma Care Traumatic injuries can occur unexpectedly due to accidents, falls, sports activities, workplace incidents, or other emergencies. View service → |